


















Article Contents
Article ID: CM2601117004
Views: 56Ion-Releasing Dental Materials: A Systematic Evidence Map of Release Kinetics, Remineralisation Proxies and Mechanical Strength Trade-offs
 PDF
⬇ Downloads: 3
1Department of Forensic Sciences, Institute of Basic Medical Sciences- Khyber Medical University, Peshawar, Pakistan
Received: 18 May, 2026
Accepted: 01 September, 2026
Revised: 14 July, 2026
Published: 14 September, 2026
ABSTRACT:
Introduction: Restorative dental materials can release fluoride, calcium, phosphate and strontium under laboratory conditions. This revised review uses a narrowed evidence-map question to examine the relationship between ion-release behaviour and mechanical strength or surface stability in ion-releasing restorative materials, and how consistently does remineralisation proxies support this relationship in vitro.
Methods: PubMed and Web of Science were searched from December 1, 2025 to January 10, 2026 for English-language in vitro and in situ studies published from 2015 to 2025. Studies were eligible when they tested a restorative material with measurable or clearly reported ion-releasing potential and reported at least one pre-specified domain: ion release, remineralisation proxy, or mechanical/surface-stability outcome. Single-domain studies were used for evidence mapping only; trade-off conclusions were drawn only from studies reporting paired ion-release and mechanical data.
Results: Eighteen studies were included. GICs/RMGICs generally showed greater early fluoride release, while alkasites, fibre-reinforced systems and selected bioactive composites showed more favourable strength or surface stability in several laboratory models. Certainty was low for laboratory remineralisation proxies and very low for clinical superiority because all included evidence was in vitro or in situ.
Conclusion: Available evidence does not recommend any specific material class for clinical use based on the current laboratory data alone. Ion release, remineralisation potential and mechanical strength should be interpreted together under the intended laboratory conditions, as improvements in one property may not necessarily translate into superior overall performance. Further clinically relevant studies are required to determine the long-term effectiveness, safety and clinical applicability of these materials.
Keywords: Ion-releasing materials, remineralisation, fluoride release, mechanical strength, bioactive dental materials.
1. INTRODUCTION
One of the most common chronic illnesses in the world is dental caries, which affects almost 3.5 billion people of all ages [1]. There has been increased emphasis on prevention and oral hygiene procedures. Nevertheless, dental caries is still one of the most serious issues for oral health systems due to its complexity and high chances of recurrence [2]. In the past, restorative dentistry aimed to restore lost tooth substance and employ comparatively inert materials, i.e. amalgam and resin composite [3]. This has redirected minimally invasive dentistry towards bio-interactive restorative materials that may incorporate structural repair and lab events that are cognizant of remineralisation and antibacterial activity [4].
In this review, restorative biomaterials capable of delivering measurable therapeutic ions like fluoride, calcium, phosphate or strontium to the oral environment under controlled laboratory conditions are called ion-releasing restorative materials. They are typified by functional behaviour in the amount of release, the duration of release and the kinetics and can be early burst release, sustained release and, in some materials, recharge using the exposed fluoride. The laboratory processes have the potential to coincide with mineral gain in demineralised enamel and dentin models; however, they should be interpreted with caution since material behaviour varies depending on formulation and test conditions [5].
To resolve the mismatch between a three-domain question and single-domain evidence, the review question was narrowed and operationalised as an evidence map.
- Primary question: What relationship is observed between ion release and mechanical strength or surface stability in ion-releasing restorative materials tested in vitro or in situ?
- Secondary questions: Which studies report ion release, remineralisation proxies, mechanical properties, or paired trade-off data; and how certain is the evidence within each material class?
Glass ionomer cements (GICs) represent some of the oldest types of ion-releasing restorative materials and release fluoride and chemically bond to enamel and dentin [6, 7]. They are described in general clinical literature in connection with conservative preparations and atraumatic restorative treatment, without any direct inference of these indications in the framework of the current evidence map. However, the conventional GICs may have lower fracture toughness, flexural strength, and wear resistance than resin composites, thereby restricting their application in high-stress-bearing restorations [8]. To give the GICs better properties in handling and earlier strength without the loss of potential fluoride release, researchers have adjusted GICs to create resin-modified GICs.
Additional bioactive restorative materials are alkasite composite restoratives, bioactive resin composite, fibre-reinforced ion-releasing composite and calcium silicate-based cement. To enhance the trade-offs between ion release, ion handling, aesthetics and mechanical stability, the following materials have been suggested [9, 10]. Materials with calcium silicate, e.g., Biodentine and TheraCal-type materials, are applied in dentine repair and endodontic localisations where the calcium release, alkalinisation, and formation of hard tissues as a barrier are critical [11].
When porosity, reduced filler loading, or hydrophilic resin matrices promote ion transport at the expense of structural integrity, highly bioactive materials can lose strength during masticatory loading [12]. This is a serious material-selection issue for restorations that are subjected to ISO-established laboratory values, particularly in the simulation of posterior occlusal loading. In order to obtain a balance between the potential to prevent and functional durability, the interdependence between the dynamics of ion release and the indicators of remineralisation and the mechanical stability has to be comprehended.
Whether oral or not also influences material behaviour; ion diffusion, surface roughness and mechanical stability might vary depending on the pH cycling, saliva composition, temperature, and oral-hygiene conditions [13]. These variables have been quantified using various laboratory models by the researchers, which include: surface microhardness, change in lesion depth, mineral gain and compressive or flexural strength. Nevertheless, complete comparisons prove challenging due to disparities between protocols and material formulations [14, 15].
The studies included failed to provide measurements of cost, placement complexities, moisture control and patient behaviour. These are contextual variables which can affect the interpretation of laboratory results in future clinical studies. GICs, bioactive composites and alkasite were also explored in the current evidence map due to their capability to couple ion release with improved mechanical or surface stability, and GICs were associated with high fluoride release. These are evidence-based laboratory trends and not clinical recommendations [7, 16].
The reason behind the necessity of this review is that most of the literature done in the past has either looked at individual material families, bioactive processes that are global or clinical applications without specifically comparing ion-release response, remineralisation parameters and mechanical trade-offs that are observed between classes of restorative materials. Consequently, clinicians might find it difficult to define the point where biological activity is preponderant over strength and where material selection should be governed by mechanical durability. This review, therefore, provides a specialized systematic review of the in vitro evidence to elucidate the balance between bioactivity and strength of restorative ion-releasing materials.
Patterns in the lab are considered to be mechanistic and hypothesis-generating until they are debunked by common ageing experiments, by in situ experiments and by clinical experiments.
2. METHODOLOGY
2.1. Study Design
This paper relied on a systematic evidence map based on PRISMA 2020. The review has not tried to procedurally subject all the studies included to all three domains. Rather, we mapped studies based on the domains that they reported, and only made direct bioactivity-strength inferences based on those that reported paired ion release and mechanical or surface stability. This method does not excessively exaggerate the results of studies that claimed only evidence of ion release, remineralisation, or mechanical properties.
The PECO framework therefore structured a narrowed question on the relationship between ion release and mechanical strength/stability, with remineralisation treated as a supporting mechanistic domain. Evidence from single-domain studies was retained for mapping, but it was not used to make direct trade-off or clinical superiority claims (Table 1).
Table 1. PECO framework.
| PICO Element | Description |
| Population (P) | Ion-releasing restorative dental materials tested in vitro or in situ |
| Exposure (E) | Bioactive, ion-releasing, alkasite, GIC/RMGIC, giomer, bioactive composite, fiber-reinforced ion-releasing or calcium-silicate formulations |
| Comparator (C) | Conventional non-ion-releasing resin composites, baseline values or within-material comparisons when no external comparator was available |
| Outcome (O) | At least one pre-specified outcome domain: numerical/directional ion release, remineralisation proxy, mechanical property or surface-stability outcome |
| Synthesis rule | Single-domain studies contributed to evidence mapping only; paired ion-release and strength/stability studies contributed to trade-off interpretation. |
2.2. Operational Definitions
For consistency, alkasite-based materials were treated as proprietary alkali-filler resin composites such as Cention N. Calcium silicate-based materials were treated as hydraulic calcium silicate materials used mainly for dentine repair, pulp-related procedures and endodontic-restorative interfaces. The term posterior restoration was used only to describe laboratory relevance to occlusal loading and ISO-related mechanical testing and not as evidence of long-term posterior clinical performance.
2.2.1. Minimum Flexural/Compressive Strength
ISO 4049 and ISO 9917 provide useful regulatory reference points for laboratory mechanical testing, but they should not be interpreted as proof of posterior clinical suitability. ISO 4049 specifies minimum flexural-strength requirements for polymer-based restorative materials [17], while ISO 9917 specifies compressive-strength requirements for water-based cements [18]. In this review, we used these values only as operational in vitro thresholds for comparing laboratory behaviour. Meeting a minimum ISO threshold does not necessarily mean that a material is suitable for large posterior restorations, where many resin composites exceed these minimum values and where fatigue, wear, fracture resistance and bonding durability are also important.
2.2.2. Minimum Ion-Release Relevance
Ion release was considered detectable when studies reported measurable fluoride, calcium, phosphate or related ions using methods such as ion-selective electrodes, spectrophotometry, chromatography, mass spectrometry or Scanning Electron Microscopy with Energy-Dispersive X-Ray Spectroscopy (SEM-EDX). The 1 µg/mm² value was treated as an internal operational cut-off where source studies reported comparable units, not as a universal clinical threshold [19]. We defined sustained release as measurable release beyond the initial 72-hour period, recognising that many materials show an early burst followed by lower release or recharge-release behaviour [20, 21].
2.3. Search Strategy
The final search was run in PubMed and Web of Science between December 1, 2025 and January 10, 2026, with the final update completed on January 10, 2026. Searches covered English-language peer-reviewed records published from January 1, 2015 to December 31, 2025. Database-specific strings combined MeSH terms, truncation, synonyms, spelling variants and material-specific names. Search strings were designed to capture studies reporting any eligible outcome domain rather than requiring all domains in the same article.
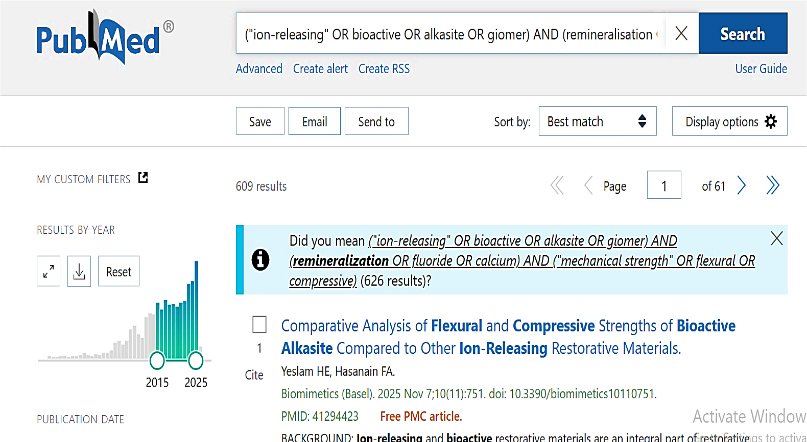
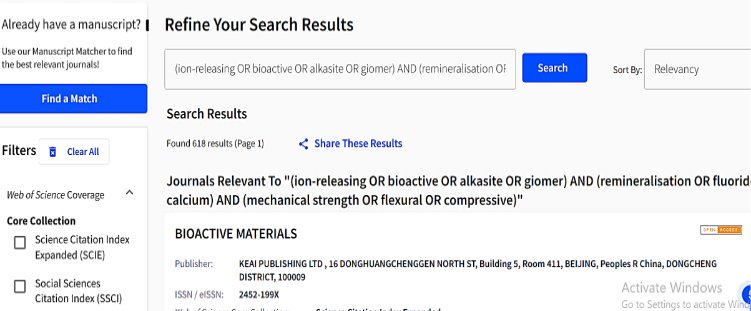
The PubMed strategy combined dental-material terms with outcome terms for ion release, remineralisation and mechanical or surface stability. The Web of Science strategy used the Topic field tags, truncation and proximity operators. Appendix 1 and Appendix 2 report the complete strings, filters, search dates, and retrieved records.
2.4. Eligibility Criteria
We revised the eligibility criteria to state the inclusion rule explicitly. Experimental in vitro or in situ studies that measured and/or clearly described the ion-releasing qualities of a restorative material and provided at least one pre-specified outcome domain, either ion release, remineralisation proxy, or mechanical/surface-stability outcome, were included.
We excluded reviews, editorials, letters, conference abstracts, and protocols, as well as clinical-only studies without extractable laboratory data and studies evaluating preventive agents without a restorative material. We also excluded studies that did not report any pre-specified outcome domains.
We retained single-domain studies because this review aimed to map the evidence. However, we used only studies reporting paired ion-release and mechanical/surface-stability outcomes to draw direct conclusions about bioactivity-strength trade-offs. We applied this rule consistently during study selection, data extraction, and synthesis (Table 2).
Table 2. Inclusion and exclusion criteria.
| Criteria | Inclusion | Exclusion |
| Study Design | Peer-reviewed in vitro or in situ experimental studies | Reviews, editorials, letters, conference abstracts, protocols, non-empirical reports and clinical-only studies without extractable laboratory data |
| Language | Published in English | Published in languages other than English |
| Type of Material | Restorative dental materials with measurable or clearly reported ion-releasing potential | Preventive agents, such as varnishes or sealants, without evaluation of a restorative material |
| Ion-Releasing Properties | Materials with reported fluoride, calcium, phosphate, strontium or related ion release/diffusion, or materials from established ion-releasing restorative classes | Materials with no plausible or reported ion-releasing mechanism and no eligible outcome domain |
| Domains of Interest | At least one domain was required: ion release, remineralisation proxy, mechanical property or surface-stability outcome. | Studies that reported none of the pre-specified domains |
| Trade-off Interpretation | Paired ion-release and mechanical/surface-stability data were required for direct trade-off conclusions | Single-domain studies were not excluded, but they were not used to infer direct bioactivity-strength trade-offs. |
| Outcome Measurement | Quantitative values or clearly reported direction of effect for extractable laboratory outcomes | Unclear methods, inadequate outcome reporting or non-extractable results |
2.5. Screening and Selection Process
Two reviewers independently screened titles and abstracts against the updated eligibility criteria after duplicate removal. Two reviewers evaluated full texts considered potentially eligible using a study-selection form documenting study design, material class, ion-release assessment and evaluation time points, eligible outcome domains, and reasons for exclusion (Appendix 3). Reviewers resolved disagreements through discussion; if they could not reach consensus, a third reviewer adjudicated.
We used Cohen’s kappa to quantify inter-reviewer agreement before consensus. Agreement was substantial for title/abstract screening (kappa = 0.82) and full-text eligibility assessment (kappa = 0.86). Reviewers resolved initial variability through discussion, supporting consistency in the screening process.
The PRISMA flow diagram (Fig. 1) shows all screening steps.
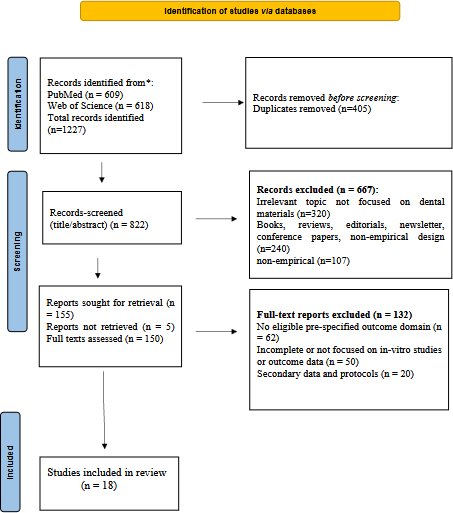
Fig. (1). PRISMA flow diagram.
We retrieved 1227 records from PubMed (n = 609) and Web of Science (n = 618). After removal of 405 duplicate records, 822 titles and abstracts were screened, and 667 records were excluded. We sought full-text reports for 155 records. We could not retrieve five reports, leaving 150 full-text reports assessed for eligibility. Of these, 132 reports were excluded because they lacked eligible pre-specified outcome domains, contained incomplete or insufficient laboratory outcome data, or represented secondary data or protocols. The final synthesis included 18 in vitro/in situ studies. The unavailability of some full texts may have introduced availability bias because negative or incompletely reported findings may be underrepresented. Although the search covered studies published from 2015 to 2025, all 18 included studies were published between 2021 and 2025.
2.6. Data Extraction Procedure
We extracted data using a predefined data extraction form (Appendix 4). Both reviewers for each study independently recorded the following information for each study: author, year, material class, comparator, storage or challenge medium, pH, time points, ion type being released (binary), ion release method (binary data), remineralisation proxy, mechanical or surface-stability outcomes, ISO reference (if reported), direction of effect, funding source, conflict of interest information (if reported) and study limitations. We extracted original numerical data without transformation. Units and experimental protocols were too heterogeneous for quantitative pooling, and findings were classified by direction of effect for evidence mapping.
The results of the database searches are presented in Appendix 5, and full-text retrieval and exclusion reasons are presented in Appendix 6. We harmonised wording to clarify the report type: report requested for retrieval; inaccessible full text; full text accessed (evaluated); and no full text available/excluded.
2.7. Quality Assessment
We evaluated study quality using the Quality Assessment Tool for In vitro Studies (QUIN). Study quality across 12 domains was assessed, such as stating the objectives, defining the sample and justifying the sample size; using a comparison or control group, randomising the group, standardising the testing process, ensuring the outcome measurement was valid, appropriate statistical analysis, complete reporting on outcomes and repeatability of the methodology. Scores for each domain ranged from 0 to 2, for a maximum total score of 24. Risk-of-bias categories were defined a priori as low risk (≥18), moderate risk (12-17) and high risk (<12). According to the predefined scoring thresholds, six studies were classified as low risk and twelve as moderate risk; none was classified as high risk. Appendix 7 includes the complete QUIN checklist and study-level scoring.
2.8. Certainty Assessment
Two additional assessments were undertaken. First, we used certainty of evidence to address whether ion-releasing restorative materials provide superior outcomes compared with conventional restorative materials. Since the evidence base comprised predominantly in vitro and in situ experimental studies rather than clinical intervention trials, the assessment was considered GRADE-informed rather than a formal GRADE assessment. ROBINS-I was not relevant as the review did not include non-randomised clinical intervention studies or clinical effect estimates, and CERQual (Confidence in the Evidence from Reviews of Qualitative Research) was not applicable as the review did not provide qualitative research findings. The certainty in the estimate was therefore assessed using a modified version of the QUIN risk of bias tool, with indirectness to clinical outcomes, inconsistency across materials/protocols, imprecision/missing numerical data and publication/availability bias. Some certainty levels were very low, low, moderate and high (Appendix 8).
2.9. Evidence Synthesis
Meta-analysis was not applicable because the included studies differed in formulation, storage media, pH, units used, outcomes evaluated, ageing conditions, and testing methods. Synthesis used standardised evidence tables, evidence mapping, vote counting by direction of effect, harvest-style matrices, and a conservative approach to apportioning confidence levels. We pooled outcomes with comparable measures only for quantitative aggregation, and only when there was no incompleteness or difference in time, duration, units, surface-area normalisation, or ageing protocols. To assess robustness, sensitivity analyses examined whether conclusions changed after excluding moderate-risk studies, single-domain studies and studies lacking numerical data. The overall interpretation remained unchanged.
4. RESULTS
4.1. Study Characteristics
The final synthesis included 18 in vitro or in situ studies published between 2021–2025. These studies involved conventional GICs, RMGICs, alkasite-based materials, bioactive resin composites, fiber-reinforced ion-releasing composites, calcium phosphate-containing composites and calcium silicate-based materials. Evidence availability varied across domains: 13 studies reported ion-release/ion-diffusion evidence, 8 reported remineralisation/mineral-proxy evidence, and 11 reported mechanical/surface-stability evidence (Tables 3 and 4). We used only studies reporting both ion release and strength or stability outcomes for direct interpretation of the bioactivity-strength trade-off. Using QUIN scoring, the final set revealed six low-risk and twelve moderate-risk studies, but no high-risk study (Appendix 7).
Table 3. Standardised evidence for domain availability and synthesis use.
| Study | Material Class | Ion-Release Data | Remineralisation Proxy | Strength/Stability Data | Synthesis Use |
| Raszewski et al., 2021 [19] | PMMA + bioactive glass/NaF | Fluoride release or recharge | Not reported | Sorption/solubility stability | Evidence map with release/stability direction |
| El-Adl et al., 2025 [20] | Ion-releasing restoratives | Fluoride release | Demineralisation inhibition/hardness | Not reported | Release-remineralisation map |
| Kasraei et al., 2022 [21] | Bioactive restorative, RMGIC, composite | Fluoride release | Not primary | Flexural strength, hardness | Direct ion-strength trade-off |
| Islam et al., 2025 [22] | GIC/RMGIC/PRG/composite | Fluoride release and recharge | Not reported | Mass stability | Release-stability trade-off |
| Aliberti et al., 2025 [23] | GIC and geriatric restorative materials | Calcium, phosphate, fluoride | Not reported | Not reported | Ion-release map only |
| Temirek 2025 [24] | Posterior restorative materials | EDX ion microanalysis | Not reported | Not reported | Ion-release map only |
| Ivica et al., 2024 [25] | Fibre-reinforced GIC | Fluoride/calcium release | Not reported | Hardness, tensile/flexural strength | Direct ion-strength trade-off |
| Yeslam & Hasanain 2025 [26] | Alkasite and ion-releasing restoratives | Not reported | Not reported | Flexural/compressive strength | Mechanical map only |
| Maaly et al., 2025 [27] | Bioactive restorative materials | Ion release | Hardness and lesion resistance | Microhardness | Release-remineralisation map |
| François et al., 2024 [28] | Ion-releasing dentin restoratives | Not extracted as release kinetics | Micro-CT dentin mineral density | Not reported | Remineralisation map only |
| Alambiaga-Caravaca et al., 2024 [29] | Fluoride-CaP flowable composites | Fluoride/CaP release | Micro-CT remineralisation | Not primary | Release-remineralisation map |
| Ibrahim et al., 2024 [30] | Ion-releasing materials under cariogenic challenge | Not measured as release kinetics | Not reported | Surface roughness/weight loss | Surface-stability map only |
| Abdelsalam et al., 2025 [31] | Ion-releasing restoration/dentin interface | Elemental ion diffusion | SEM-EDX interface proxy | Not reported | Interface/rem. map only |
| Puttipanampai et al., 2025 [32] | Fluoride-releasing materials adjacent to enamel | Not extracted as kinetics | Enamel microhardness | Not reported | Remineralisation map only |
| Llancari-Alonzo et al., 2024 [33] | Four ion-releasing restoratives | Fluoride release | Not reported | Flexural strength | Direct ion-strength trade-off |
| Garoushi et al., 2022 [34] | Ion-releasing fiber-reinforced composite | Calcium release | Interfacial mineralisation/SEM-EDS | Flexural strength/toughness | Direct ion-strength trade-off |
| Garoushi et al., 2025 [35] | Restorative materials after ageing | Fluoride release | Not reported | Flexural strength after ageing | Direct ion-strength trade-off |
| Radwanski et al., 2025 [36] | Modern bioactive restoratives | Not reported | Not reported | Strength, modulus, hardness, sorption | Mechanical map only |
Table 4. Evidence by reported outcome domains.
| Evidence Domain | Studies (N) | How they are Used in Synthesis |
| Ion release/ion diffusion | 13 | Mapped by ion type, material class, method and direction; pooled only if units/time points were comparable |
| Remineralisation or mineral-proxy outcomes | 8 | Interpreted as indirect laboratory evidence; not treated as clinical caries-prevention proof |
| Mechanical or surface-stability outcomes | 11 | Mapped by strength, hardness, roughness, weight loss or ageing stability |
| Paired ion-release with strength or stability outcomes | 6 | Used for direct bioactivity-strength trade-off interpretation |
| Single-domain studies | 5 | Used for evidence mapping only; not used to infer trade-offs or clinical superiority |
3.2. Vote Counting, Effect Direction and Confidence Mapping
Vote counting was used only to summarise the direction of laboratory effects, not to estimate effect size. A positive direction means the ion-releasing material showed higher ion release, a stronger remineralisation proxy, or a stronger/more stable mechanical outcome than its comparator or baseline within the source study. A mixed direction means benefit in one domain was accompanied by weakness in another. Table 5 summarises these patterns by material class.
Table 5. Outcomes of material classes.
| Material Class | Ion-Release Direction | Remineralisation Direction | Mechanical/Stability Direction | Overall Evidence Pattern | Confidence |
| Conventional GIC/RMGIC | + for early fluoride release | +/mixed for remineralisation proxies | -/mixed for strength and surface stability | High release but frequent durability trade-off | Low |
| Alkasite materials | +/moderate release | +/mixed proxy support | +/mixed strength compared with GIC | More balanced laboratory profile than conventional GIC in several studies | Low |
| Bioactive composites/PRG systems | +/moderate release | +/mixed proxy support | +/mixed surface stability | Formulation-dependent; not uniformly superior | Low |
| Fibre-reinforced ion-releasing systems | + for Ca/F release when measured | + interface proxy in limited data | + for toughness/strength in limited data | Promising paired profile, but few studies | Low to very low |
| Calcium silicate/CaP formulations | + for Ca/P-related release or deposition | + for dentin/enamel proxy outcomes | Not consistently tested for restorative load-bearing strength | Mechanistic potential, weak load-bearing evidence | Very low |
Note: + = favourable/positive direction relative to the comparator or baseline; − = unfavourable/negative direction
Abbreviation: GIC = Glass Ionomer Cement; RMGIC = Resin-Modified Glass Ionomer Cement; PRG = Pre-Reacted Glass.
Among studies that reported ion-release or ion-diffusion outcomes, release was strongly material-dependent. Fluoride was the most frequently reported ion, while calcium, phosphate and strontium were less consistently measured. GICs and RMGICs usually showed greater early fluoride release, whereas alkasites, PRG-based materials and selected bioactive composites showed lower, sustained or formulation-dependent release patterns.
We considered quantitative aggregation of fluoride release, calcium release, flexural strength, and compressive strength. However, we did not perform quantitative synthesis because studies used different units, exposure surfaces, time points, pH, media, recharge protocols, and ageing conditions. This heterogeneity would make a pooled mean misleading. Therefore, the numerical synthesis was restricted to extracting reported values where available, direction-of-effect coding, and class-level patterns. Future updates should predefine common units such as microgram/mm2/day or ppm at matched time points and should extract flexural/compressive strength in MPa after matched ageing periods.
3.3. Ion Release Characteristics
3.3.1. Fluoride Release and Recharge Behaviour
Fig. (2) summarises the main fluoride-release pattern observed across the included evidence map. Because units, exposure surfaces, recharge protocols and time points differed, the figure is presented as a direction-only visual synthesis rather than a pooled quantitative comparison.
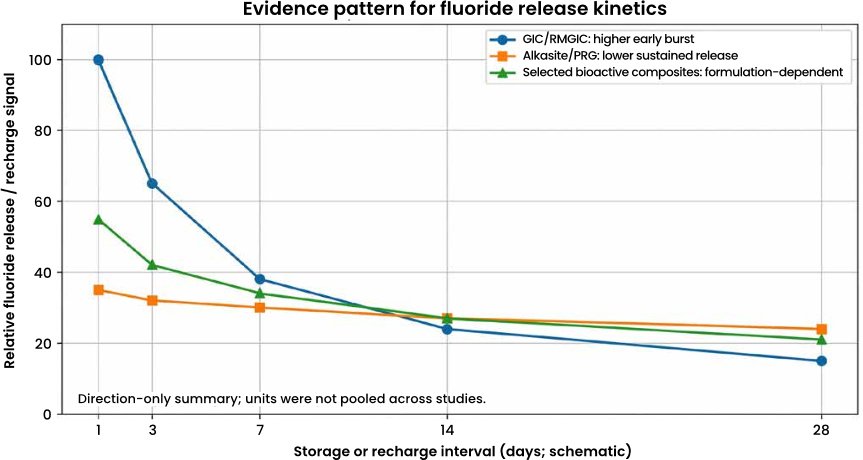
Fig. (2). Schematic summary of fluoride-release patterns across included ion-releasing restorative-material studies. the figure is not a pooled effect estimate because units and protocols differed across studies.
Across studies reporting ion release or ion diffusion, release profiles were material dependent. Conventional GICs/RMGICs most consistently showed a pronounced early fluoride-release signal, while alkasites, PRG-based systems, and selected bioactive composites generally showed lower, sustained or formulation-dependent patterns. Confidence in this pattern remains low because release units, media and observation periods differed across studies [19, 21–24, 27, 33].
Across fluoride-release studies, the common kinetic pattern was an initial release phase followed by lower continued release or recharge-related behaviour. Therefore, we considered release kinetics and durability-related outcomes together rather than ranking materials only by total fluoride quantity [19, 20, 22].
Fig. (2) represents storage or recharge intervals (x-axis) against relative release signal (y-axis).
Overall, multi-ion release may support a longer laboratory remineralisation window, but its value depends on whether the material also maintains surface stability and adequate mechanical strength. Higher ion release alone was not treated as evidence of clinical superiority.
3.3.2. Multi-Ion Release and Material-Dependent Variability
Across studies assessing calcium, phosphate, fluoride or elemental ion diffusion, multi-ion release was most evident in GICs, alkasites, fluoride-doped calcium-phosphate composites and related bioactive formulations. These studies collectively indicated broader ionic profiles than fluoride-only systems, but confidence remains low because formulations, analytical methods and storage conditions differed substantially [23, 24, 27, 28, 29, 31].
At class level, GIC-based materials tended to show stronger early release, whereas alkasite-based materials and selected fluoride-releasing composites showed lower or more sustained release signals. These are laboratory patterns only and should not be interpreted as evidence that any class has confirmed clinical superiority [25, 26, 33].
Overall, multi-ion release may support a longer in vitro remineralisation window. Still, its value depends on whether the material also maintains surface stability and adequate mechanical strength under acidic challenge.
3.3.3. Calcium and Phosphate Release Supporting Remineralisation
Most remineralisation studies used indirect laboratory outcomes such as surface microhardness, mineral deposition, micro-CT mineral-density change, lesion-depth reduction or SEM-EDX elemental evidence. These outcomes support mechanistic plausibility, but they do not prove reduced secondary caries, longer restoration survival or direct clinical benefit.
3.3.4. Influence of Environmental pH on Ion Release
Environmental pH influenced both diffusion and surface behaviour. Acidic conditions increased ion release in several models [31, 32], which is relevant to cariogenic challenge. However, the same acidic conditions can also accelerate degradation in vulnerable materials. For this reason, ion-release results were interpreted together with surface stability rather than treated as a standalone measure of material performance.
3.4. Remineralisation Potential
3.4.1. Assessment of Remineralisation Outcomes
Most included studies assessed remineralisation using indirect laboratory outcomes such as surface microhardness, mineral deposition, micro-CT mineral-density change, lesion-depth reduction or SEM-EDX evidence of mineral deposition. These indicators are useful for comparing materials in vitro, but they should not be interpreted as direct proof of clinical caries prevention.
3.4.2. Enamel and Dentin Remineralisation Evidence
In remineralisation-proxy studies, positive laboratory signals were obtained by either enamel or dentin microhardness, or by mineral-density change or by a reduction in lesion depth and mineralization at the material-tooth interface. In studies where fluoride release was coupled with calcium/phosphate availability, these results were more reproducible but not directly comparable because of different lesion models and exposure durations [21, 28, 29, 32, 33].
3.4.3. Interfacial Ion Diffusion and Subsurface Remineralisation
Interfacial studies using SEM-EDX supported elemental ion diffusion or deposition near the dentin-restoration interface. However, these findings were treated as indirect surface/interface evidence rather than proof of functional remineralisation or clinical lesion arrest [27, 31].
3.4.4. SEM-EDX Evidence of Bioactivity at the Material-Dentin Interface
Mechanical integrity remained essential for interpreting restorative relevance. The main mechanical or surface-stability outcomes were flexural strength, compressive strength, hardness, roughness, weight loss, sorption and degradation behaviour. Conventional GICs often released more fluoride but did not consistently show the strongest flexural, compressive or ageing performance compared with resin-based, alkasite or reinforced alternatives.
SEM-EDX provides qualitative or semi-quantitative compositional information and does not measure longitudinal ion flux. Therefore, we interpreted SEM-EDX findings alongside micro-CT and microhardness outcomes to strengthen mechanistic interpretation without converting proxy evidence into clinical claims. Fig. (3) illustrates the type of elemental evidence considered in this domain.
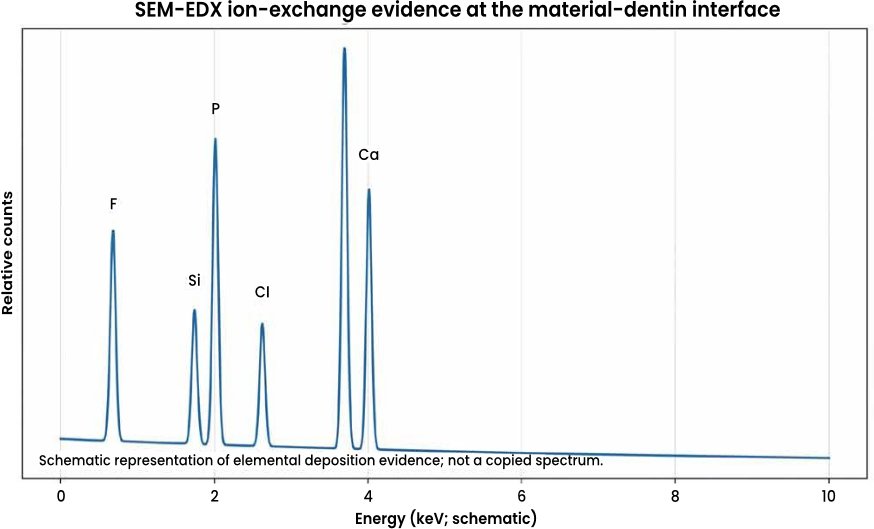
Fig. (3). Schematic representation of SEM-EDX elemental ion-exchange evidence at the material-dentin interface. The figure illustrates the evidence type discussed in Abdelsalam et al., [31] and is not a copied spectrum.
3.5. Mechanical Properties and Strength Trade-Offs
3.5.1. Evaluation of Mechanical Strength Parameters
Although ion release and remineralisation markers are desirable, mechanical integrity remains essential for restorative survival. The main mechanical outcomes assessed across the included studies were compressive strength, flexural strength, surface hardness and degradation behaviour. Conventional GICs often showed strong ion release but lower flexural and compressive performance than resin-based or reinforced alternatives [21, 34].
3.5.2. Surface Integrity, Degradation, and Cariogenic Challenges
Across surface-stability studies, acidic or cariogenic challenge tended to increase roughness, mass change or degradation in more vulnerable ion-releasing materials. Materials with stronger ion release did not necessarily show the strongest surface stability, which supports a class-level trade-off between diffusion-friendly chemistry and durability under challenge conditions [24, 30, 36].
3.6. Cross-Study Synthesis: Patterns, Contradictions and Certainty
The strongest cross-study pattern was a bioactivity-strength trade-off. Materials with higher early fluoride release, especially conventional GICs, often showed weaker or more vulnerable mechanical/surface-stability profiles. Conversely, resin-based bioactive and alkasite materials frequently showed stronger mechanical behaviour but not always the highest ion release. This supports a relationship between matrix permeability, filler chemistry and strength. Water movement can promote ion diffusion, but excessive hydrophilicity, porosity or filler dissolution can compromise durability.
Contradictions were also present. Acidic challenge often increased measured ion release, but the same challenge could increase roughness, solubility or degradation. Micro-CT and SEM-EDX studies supported mineral deposition or density changes [28, 29, 31], but radiopacity, short exposure times and different lesion models limited comparability. Therefore, the evidence supports mechanistic plausibility more strongly than it supports material ranking or clinical claims. An exploratory quantitative ranking of material classes based on these directional patterns is summarised in Appendix 9 for illustrative purposes only.
4. DISCUSSION
4.1. Mechanistic Interpretation Framework
The mechanistic interpretation framework links material chemistry to observed laboratory outcomes. It is not a validated clinical framework; it is a transparent way to explain why ion release and strength may move in opposite directions. Table 6 summarises this framework, along with the evidence direction and certainty for each mechanistic question.
Table 6. Mechanistic framework.
| Mechanistic Stage | Laboratory Indicator | Expected Benefit | Potential Trade-Off |
| Filler/matrix chemistry | Glass ionomer, PRG, alkasite, CaP, bioactive glass or calcium silicate composition | Source of fluoride, calcium, phosphate, strontium or other ions | Hydrophilic or porous matrices may reduce strength |
| Water uptake and diffusion | Storage medium, pH cycling, recharge protocol | Enables ion movement and recharge | May increase sorption, solubility or roughness |
| Ion release at interface | ISE, spectrophotometry, chromatography, ICP/MS or SEM-EDX | Supports local mineral availability | Burst release may decline quickly |
| Tooth-substrate response | Microhardness, lesion depth, micro-CT, SEM-EDX | Suggests remineralisation proxy effect | Proxy outcome may not predict clinical caries prevention |
| Restorative durability | Flexural/compressive strength, hardness, wear, mass loss | Maintains function under load | Higher bioactivity may coincide with weaker stability |
| Question | Evidence direction | Main limitation | Certainty |
| Do ion-releasing materials release more therapeutic ions than conventional composites? | Generally yes in laboratory studies reporting release | Units, media and time points differed | Low |
| Do they improve remineralisation proxies? | Often positive but proxy-dependent | Microhardness, micro-CT and SEM-EDX are indirect outcomes | Low |
| Do they outperform conventional materials mechanically? | Not consistently; some are weaker, some are comparable or stronger | Different ageing protocols and few direct comparisons | Very low to low |
| Do they outperform conventional materials clinically? | Not answerable from this review | No clinical survival or secondary-caries outcomes analysed | Very low |
Abbreviation: CaP: calcium phosphate; PRG = Pre-Reacted Glass; ISE = Ion-Selective Electrode; ICP/MS = Inductively Coupled Plasma Mass Spectrometry; SEM-EDX = Scanning Electron Microscopy with Energy-Dispersive X-Ray Spectroscopy
4.2. Trade-Off Between Bioactivity and Structural Stability
Fig. (4) summarises the direction of surface roughness and degradation findings after exposure to reference, storage and cariogenic challenge conditions. The figure is presented as a direction-only synthesis because source studies used heterogeneous materials, media and outcome units. The underlying studies were not statistically pooled or compared because of differing units, protocols and outcome measures; therefore, no error bars or p-values are presented, and the bars reflect the direction of effect only, not tested statistical significance.
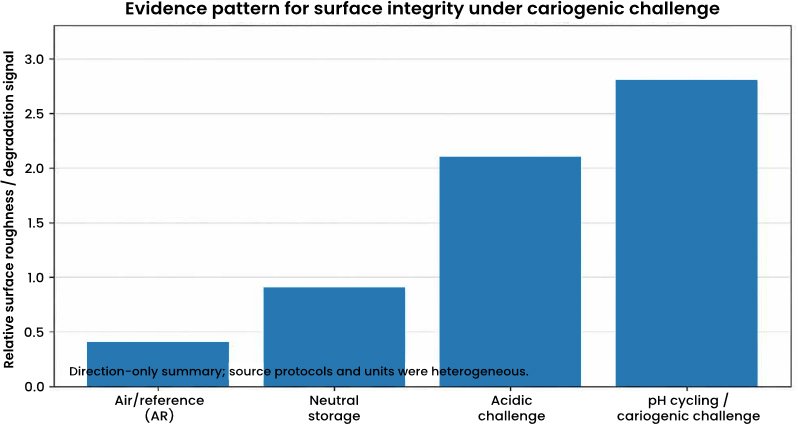
Fig. (4). Direction-only schematic summary of surface roughness/degradation patterns under cariogenic or acidic challenge. Values are illustrative of evidence direction only and are not pooled data.
The observed trade-off is best explained as a material-chemistry issue rather than a simple ranking of materials. Water uptake, matrix permeability and filler dissolution can create pathways for fluoride, calcium and phosphate diffusion. The same pathways may increase sorption, solubility, surface roughness or strength loss after acidic challenge. Resin reinforcement, fibre reinforcement and alkasite or PRG filler systems may reduce some durability losses, but lower permeability can also reduce ion movement. This helps explain why the synthesis prioritised paired ion-release and strength/surface-stability data.
4.3. Evidence Translation Framework: Laboratory Findings and Potential Clinical Relevance
The framework below translates laboratory findings into research-relevance areas. It does not identify indicated uses or preferred materials; instead, it shows which clinical questions could reasonably be tested next and which inferences remain outside the included evidence. Table 7 summarises this translation framework. In laboratory models, recent advancements such as s-PRG fillers, nano-amorphous calcium phosphate composites, pH-responsive ion-release systems, and bioactive-glass resin composites remain promising. However, nanoparticle agglomeration, water sorption, polish retention, colour stability, and fatigue and wear should be explored more thoroughly in longer-term ageing and clinical follow-up studies before performance claims can be made.
Table 7. Translation of the laboratory findings.
| Potential Relevance Area | Laboratory Findings from Included Studies | Research Implication | Boundary of Inference |
| Conservative or moisture-sensitive placement models | GIC/RMGIC fluoride release was frequent; moisture tolerance was background context rather than a directly tested outcome. | Future studies can test whether release profiles matter under isolation or minimal-intervention conditions. | The authors make no recommendation for pediatric or minimally invasive use. |
| Simplified-placement or ART-style research settings | Fluoride release and simple placement were plausibility factors discussed in background literature, but restoration survival was not measured. | Pair release data with restoration survival, marginal integrity and failure in pragmatic studies. | Laboratory release does not establish ART effectiveness. |
| Caries-risk and demineralisation models | Ion release and remineralisation proxies were positive in some acidic or pH-cycling models. | Test secondary-caries and lesion-arrest outcomes in clinical or in situ designs. | No patient-level reduction in secondary caries was measured. |
| Load-bearing restorative models | Alkasite, reinforced or selected bioactive materials showed favourable strength or surface stability in some in vitro tests. | Use longer-term ageing, fatigue and wear protocols with paired release data. | Short-term ISO or MPa thresholds do not prove posterior durability. |
| Dentin-interface or material-tooth interface models | Limited studies reported calcium/phosphate deposition and SEM-EDX interface signals. | Combine interface imaging with bonding durability and clinical follow-up. | Proxy deposition does not prove functional dentin regeneration. |
Abbreviation: GIC = glass ionomer cement; RMGIC = resin-modified glass ionomer cement; ART = Atraumatic Restorative Treatment; MPa = megapascal; SEM-EDX = Scanning Electron Microscopy with Energy-Dispersive X-Ray Spectroscopy
4.4. Comparison with Previous Systematic Reviews and Mechanistic Implications
The current evidence map broadly supports the mechanistic patterns described in previous reviews while applying more conservative interpretations. Related laboratory work has also used micro-computed tomography and scanning electron microscopy to evaluate mineral changes in initial caries and erosive lesion models [37]. Wiegand et al., [38] discussed fluoride-releasing restorative materials and highlighted that fluoride release/recharge and antibacterial properties depend on restorative type, filler type, and environmental factors. Nicholson et al., also reported early wash-out, diffusion, recharge, and acidic conditions as important factors affecting glass-ionomer fluoride exchange [39]. Tokarczuk et al., [40] systematically reviewed surface-coating effects and concluded that coatings generally influence fluoride release, with glass-ionomer materials showing the highest early release.
This review builds on these findings by extending the focus from release quantity alone to release behaviour, strength, roughness, solubility, and ageing outcomes. Biologically, fluoride may contribute to a less soluble mineral phase, influence bacterial acid metabolism, and support calcium and phosphate availability for deposition of apatite-like mineral phases in demineralised substrates. Mechanistically, the water-mediated diffusion required for ion transport may also weaken susceptible matrices or accelerate surface degradation. Accordingly, the principal implication is not to rank materials, but to evaluate ion-release kinetics, remineralisation proxies and durability concurrently under matched ageing conditions.
LIMITATIONS OF THE STUDY
The main limitation of this review is that the included evidence was predominantly laboratory-based and therefore indirect for clinical practice. Material composition, storage media, pH challenge, measurement timing, specimen dimensions and outcome units were heterogeneous, which prevented reliable meta-analysis. Publication and availability bias are possible because inaccessible full texts, negative laboratory findings and industry-internal data may be under-represented. The English-language restriction may also have excluded relevant studies. Sensitivity checks did not change the overall interpretation; the evidence supports laboratory ion release and proxy remineralisation, but not clinical superiority or universal mechanical advantage.
STRENGTHS OF THE STUDY
This review’s strength is that it separates evidence mapping from direct trade-off interpretation. It uses predefined eligibility criteria, structured data extraction, QUIN-based quality assessment, adapted certainty assessment, vote counting and standardised evidence tables. This approach makes the synthesis more transparent and reduces the risk of drawing clinical conclusions from single-domain laboratory findings.
CHALLENGES AND FUTURE DIRECTIONS
Future studies should aim to identify ion-releasing material systems that preserve fatigue and wear resistance as well as surface stability. Ion-release outcomes, remineralisation proxies and mechanical ageing should be compared quantitatively between material classes using standardised protocols.
Laboratory ion-release and remineralisation findings should be complemented by long-term in situ studies and validated through randomised clinical and practice-based evaluations. Future studies should report standardised units, matched time points, specimen dimensions, pH-cycling protocols, paired strength and surface-stability outcomes and recharge conditions. Smart-release systems and nano-bioactive composites remain promising laboratory developments. Still, longer-term ageing and wear evidence, together with clinical follow-up, is required before performance claims can be made.
CONCLUSION
Ion-releasing dental materials demonstrate laboratory mechanisms relevant to caries prevention, including therapeutic ion release and remineralisation-related proxy effects. These biological signals must be interpreted together with mechanical and surface-stability outcomes, especially where restorations are exposed to occlusal load or acidic challenge. Current evidence does not justify routine preference of one material class over another, although laboratory findings suggest that certain materials may be advantageous under specific experimental conditions. No single material class showed ideal performance across ion release, remineralisation and mechanical strength. More standardised in vitro, in situ and clinical studies are needed before firm long-term clinical claims can be made.
LIST OF ABBREVIATIONS
ART | = | Atraumatic Restorative Treatment |
GICs | = | Glass Ionomer Cements |
Micro-CT | = | Micro-Computed Tomography |
MPa | = | Megapascal |
PRG | = | Pre-Reacted Glass. |
PRG | = | Surface Pre-Reacted Glass-ionomer |
QUIN | = | Quality Assessment Tool for In vitro Studies |
RMGICs | = | Resin-Modified Glass Ionomer Cements |
SEM-EDX | = | Scanning Electron Microscopy with Energy-Dispersive X-ray Spectroscopy |
s-PRG | = | Surface Pre-Reacted Glass-ionomer |
AUTHOR’S CONTRIBUTION
W.A. conceptualized the study, conducted the analysis and interpretation and wrote the manuscript.
REPORTING GUIDELINES
PRISMA guidelines have been followed for this study.
FUNDING
No research grant was provided for conducting this research.
CONFLICT OF INTEREST
The author declares no conflict of interest.
ACKNOWLEDGEMENTS
The author would like to acknowledge the guidance and support received from faculty members and peers throughout the course of this research project.
DECLARATION OF AI
The author used the AI tool (ChatGPT) for final editing of the manuscript and take responsibility for the published content.
APPENDICES
Appendix 1. PubMed and Web of Science.
Appendix 2. Database-Specific Search Strings and Search Dates.
| Database | Complete Search Strategy | Filters and Date Run | Results |
| PubMed | ((“Dental Materials”[Mesh] OR “Glass Ionomer Cements”[Mesh] OR “Composite Resins”[Mesh] OR restorative material*[tiab] OR dental material*[tiab] OR glass ionomer*[tiab] OR GIC[tiab] OR RMGIC[tiab] OR giomer*[tiab] OR alkasite*[tiab] OR “Cention N”[tiab] OR “Activa Bioactive”[tiab] OR “bioactive composite*”[tiab] OR “calcium silicate”[tiab] OR Biodentine[tiab] OR TheraCal[tiab]) AND ((“Tooth Remineralization”[Mesh] OR remineralization[tiab] OR remineralisation[tiab] OR fluoride[tiab] OR calcium[tiab] OR phosphate[tiab] OR strontium[tiab] OR “ion release”[tiab] OR recharge[tiab]) OR (“Flexural Strength”[Mesh] OR flexural[tiab] OR compressive[tiab] OR hardness[tiab] OR wear[tiab] OR “surface roughness”[tiab] OR degradation[tiab] OR “mechanical propert*”[tiab]))) | English; 2015-2025; final update 10 Jan 2026 | 609 |
| Web of Science | TS=((dental NEAR/3 material* OR restorative NEAR/3 material* OR “glass ionomer*” OR GIC OR RMGIC OR giomer* OR alkasite* OR “Cention N” OR “Activa Bioactive” OR “bioactive composite*” OR “calcium silicate*” OR Biodentine OR TheraCal) AND ((ion* NEAR/3 release OR fluoride OR calcium OR phosphate OR strontium OR recharge OR remineralisation OR remineralization) OR (flexural OR compressive OR hardness OR wear OR “surface roughness” OR degradation OR “mechanical propert*”))) | English; 2015-2025; final update 10 Jan 2026 | 618 |
Appendix 3. Study Selection Form.
| Screening item | Response options |
| Study design | In vitro / in situ / clinical-only / review / editorial / conference / protocol |
| Material type | Restorative ion-releasing material / preventive-only agent / non-restorative material |
| Outcome domain reported | Ion release / remineralisation proxy / mechanical property / surface stability / none |
| Comparator | Conventional composite / other ion-releasing material / baseline / no comparator |
| Include? | Yes if restorative material plus at least one eligible domain; otherwise exclude with reason |
Appendix 4. Data Extraction Form.
| Extraction Field | Details Recorded |
| Bibliographic data | Author, year, country, journal, funding/conflicts if reported |
| Material and comparator | Brand/class, composition, ion-releasing mechanism, control material |
| Test conditions | Medium, pH, temperature, storage/recharge time points, ageing or pH cycling |
| Ion release | Ion type, method, units, time point, numerical value or direction of effect |
| Remineralisation proxy | Microhardness, lesion depth, micro-CT, SEM-EDX or mineral density outcome |
| Mechanical/stability outcome | Flexural/compressive strength, hardness, roughness, wear, weight loss, sorption or degradation |
| Synthesis coding | Domain availability, paired trade-off status, effect direction, certainty concerns |
Appendix 5. Search Outcomes.
| Stage | PubMed | Web of Science | Total (n) |
| Records identified from databases | 609 | 618 | 1227 |
| Duplicates removed | 203 | 202 | 405 |
| Records screened after duplicates | 406 | 416 | 822 |
| Records excluded at title/abstract | 330 | 337 | 667 |
| Irrelevant topic not focused on dental materials | 160 | 160 | 320 |
| Books, reviews, editorials, newsletters, conference papers | 120 | 120 | 240 |
| Other non-empirical reasons | 50 | 57 | 107 |
| Reports sought for retrieval | 75 | 80 | 155 |
| Reports not retrieved | 2 | 3 | 5 |
| Full-text reports assessed | 73 | 77 | 150 |
| Reports excluded at full text | 65 | 67 | 132 |
| Studies included in final review | 8 | 10 | 18 |
Appendix 6. Full-Text Retrieval Outcomes and Exclusion Reasons.
| Full-Text Outcome | Pubmed | Web Of Science | Total (N) |
| Reports not retrieved / full text unavailable | 2 | 3 | 5 |
| No eligible pre-specified outcome domain | 30 | 32 | 62 |
| Incomplete laboratory methods or non-extractable outcome data | 25 | 25 | 50 |
| Secondary data and protocols | 10 | 10 | 20 |
| Reports excluded after full-text assessment | 65 | 67 | 132 |
| Included in final synthesis | 8 | 10 | 18 |
Appendix 7. QUIN Critical Appraisal Checklist (Quality Assessment of Included In vitro Studies).
| Study | QUIN Score (/24) | Risk of Bias | Main Certainty Concern |
| Raszewski et al., 2021 [19] | 17 | Moderate | No blinding/randomisation; limited paired outcomes |
| El-Adl et al., 2025 [20] | 16 | Moderate | Short-term fluoride/remineralisation proxy |
| Kasraei et al., 2022 [21] | 18 | Low | Short-term laboratory conditions |
| Islam et al., 2025 [22] | 16 | Moderate | Mass stability and release units heterogeneous |
| Aliberti et al., 2025 [23] | 18 | Low | Ion release only; no mechanical outcome |
| Temirek 2025 [24] | 16 | Moderate | EDX microanalysis; limited strength pairing |
| Ivica et al., 2024 [25] | 18 | Low | Modified material; limited clinical indirectness |
| Yeslam & Hasanain 2025 [26] | 16 | Moderate | Mechanical-only evidence |
| Maaly et al., 2025 [27] | 16 | Moderate | Proxy remineralisation outcome |
| François et al., 2024 [28] | 16 | Moderate | Micro-CT proxy and radiopacity concerns |
| Alambiaga-Caravaca et al., 2024 [29] | 16 | Moderate | Experimental material and proxy outcome |
| Ibrahim et al., 2024 [30] | 16 | Moderate | Surface-stability outcome only |
| Abdelsalam et al., 2025 [31] | 16 | Moderate | SEM-EDX interface proxy only |
| Puttipanampai et al., 2025 [32] | 16 | Moderate | Remineralisation proxy only |
| Llancari-Alonzo et al., 2024 [33] | 16 | Moderate | Limited time points and comparator variation |
| Garoushi et al., 2022 [34] | 19 | Low | Few comparable formulations |
| Garoushi et al., 2025 [35] | 18 | Low | Ageing model not clinical survival |
| Radwanski et al., 2025 [36] | 18 | Low | Mechanical-only evidence |
Appendix 8. Certainty Assessment Form.
| Domain | Judgement Applied in This Review |
| Risk of bias | QUIN low/moderate/high risk |
| Indirectness | Downgraded because in vitro/in situ outcomes do not directly measure clinical survival or caries prevention |
| Inconsistency | Downgraded when directions differed by material, medium, pH or ageing protocol |
| Imprecision | Downgraded when numerical data, standard deviations or sample-size justification were missing |
| Publication/availability bias | Downgraded when full texts were unavailable or negative/unpublished laboratory data were plausible |
| Overall certainty | High / moderate / low / very low, with clinical superiority rated very low |
Appendix 9. Exploratory Quantitative Ranking Model and Laboratory Decision Matrix.
| Material class/example | Ion-release score | Remineralisation-proxy score | Mechanical/stability score | Total (/6) | Laboratory-only interpretation |
| Cention N / alkasite | 2 = higher or sustained release in included studies | 1-2 = positive proxy in limited studies | 2 = stronger than GIC in several tests | 5-6 | Balanced laboratory profile; not proof of clinical superiority |
| Activa / selected bioactive composites | 1-2 = formulation-dependent release | 1 = limited proxy evidence | 1-2 = variable ageing stability | 3-5 | Promising but inconsistent; needs paired long-term data |
| Conventional GIC / Fuji II LC | 2 = strong early fluoride release | 1 = supportive proxy evidence | 0-1 = weaker strength/surface stability in several tests | 3-4 | High release with durability trade-off in vitro |
| Fibre-reinforced ion-releasing systems | 1-2 = Ca/F release in limited studies | 1 = limited interface proxy | 2 = improved toughness/strength in limited studies | 4-5 | Potentially balanced, but evidence base is small |
| Calcium silicate/CaP systems | 2 = Ca/P-related release/deposition | 2 = strong mechanistic proxy | 0-1 = insufficient restorative load-bearing data | 4-5 | Useful mechanistic signal; not evidence for stress-bearing restorations |
| Zirconomer / high-strength GIC variants | 1 = material-dependent release | 0-1 = limited remineralisation proxy | 1-2 = stronger than conventional GIC in limited data | 2-4 | Mechanical promise varies; evidence not enough for clinical ranking |
Note: Scoring rule: 0 = absent/negative evidence, 1 = mixed or limited evidence, 2 = consistently favourable laboratory evidence within the included studies. Scores were assigned independently by two reviewers from extracted direction-of-effect data and reconciled by consensus. The model is exploratory, not externally validated, and must not be used as a stand-alone clinical recommendation.
REFERENCES
[1] World Health Organization. Oral health [Internet]. Geneva: World Health Organization; 2025 [cited 2026 Jun 22]. Available from: https://www.who.int/news-room/fact-sheets/detail/oral-health
[2] Duangthip D, Chu CH. Challenges in oral hygiene and oral health policy. Front Oral Health. 2020; 1: 575428.
https://doi.org/10.3389/froh.2020.575428
[3] Moraes RR, Cenci MS, Moura JR, Demarco FF, Loomans B, Opdam N. Clinical performance of resin composite restorations. Curr Oral Health Rep. 2022;9: 22-31.
https://doi.org/10.1007/s40496-022-00308-x
[4] Sauro S, Carvalho RM, Ferracane J. The rise of advanced bioactive restorative materials: Are they redefining operative dentistry? Dent Mater. 2025;41(11): 1411-1429.
https://doi.org/10.1016/j.dental.2025.08.003
[5] Sajini S. Fundamentals of dentine demineralization and remineralization with the role of bioactive materials in dentine regeneration. J Biochem Technol. 2023;14(2): 94-101.
https://doi.org/10.51847/S0ffgkKuQW
[6] Mohanty S, Kalimireddy PL. Evolution of modified glass ionomer cements: A review. Indian J Forensic Med Toxicol. 2020;14(4): 8762-4.
https://doi.org/10.37506/ijfmt.v14i4.13086
[7] Ge KX, Lam WY-H, Chu C-H, Yu OY. Updates on the clinical application of glass ionomer cement in restorative and preventive dentistry. J Dent Sci. 2024; 19(Suppl 1): S1-S9.
https://doi.org/10.1016/j.jds.2024.07.021
[8] Sikka N, Brizuela M. Glass ionomer cement. In: StatPearls Publishing; 2022. Available from: https://www.ncbi.nlm.nih.gov/books/NBK582145/
[9] Abozaid D, Azab A, Bahnsawy MA, Eldebawy M, Ayad A, Soomro R, Elwakeel E, Mohamed MA. Bioactive restorative materials in dentistry: A comprehensive review of mechanisms, clinical applications, and future directions. Odontology. 2026;114(2):349-77.
https://doi.org/10.1007/s10266-025-01162-w
[10] Antoanela MC, Andrei M, Dinca I, Ciocan LT, Matei MN, Didilescu AC. Tertiary dentin barrier formation: A comparison between the effects of two calcium silicate-based materials. Curr Health Sci J. 2025;51(1): 96-104. Available from: https://pubmed.ncbi.nlm.nih.gov/40678306/
[11] Chaudhari PS, Chandak MG, Jaiswal AA, Mankar NP, Paul P. A breakthrough in the era of calcium silicate-based cements: a critical review. Cureus. 2022;14(8): e28562.
https://doi.org/10.7759/cureus.28562
[12] Pandey A. Recent advances in bioactive dental materials: a paradigm shift in restorative dentistry. Dental. 2024;6(2): 15.
https://doi.org/10.35702/dent.10015
[13] Kainaat B, Alam SD, Hussain A, Farooq A, Malik AA. Effects of pH and temperature on dental materials in saliva and oral fluids. Int J Pharm Res Technol. 2025;15(2): 449-55. Available from: https://www.researchgate.net/publication/394367448_Effects_of_ph_and_Temperature_on_Dental_Materials_in_Saliva_and_Oral_Fluids
[14] Dohan Z, Friedlander LT, Cooper PR, Li KC, Ratnayake JT, Mei ML. In vitro models used in the formation of root caries lesions: A review of the literature. Dent J (Basel). 2023;11(12): 269.
https://doi.org/10.3390/dj11120269
[15] Hammel C, Pandis N, Pieper D, Faggion CM. Methodological assessment of systematic reviews of in vitro dental studies. BMC Med Res Methodol. 2022;22(1): 110.
https://doi.org/10.1186/s12874-022-01575-z
[16] Ikram AM, Mohamad D, Shahzad A, Kausar R, Iqbal A, Riaz A. Bioactive composites in dentistry: A comparative study of tissue regeneration, biological activity, and clinical outcomes in various dental applications. J Neonatal Surg. 2025;14(32 Suppl): 8772-8777.
https://doi.org/10.63682/jns.v14i32S.9311
[17] International Organization for Standardization. ISO 4049:2009 Dentistry – polymer-based restorative materials. Geneva: ISO; 2009. Available from: https://www.iso.org/standard/42898.html
[18] International Organization for Standardization. ISO 9917-1:2007 Dentistry – water-based cements – Part 1: powder/liquid acid-base cements. Geneva: ISO; 2007. Available from: https://www.iso.org/standard/45818.html
[19] Raszewski Z, Nowakowska D, Wieckiewicz W, Nowakowska-Toporowska A. Release and recharge of fluoride ions from acrylic resin modified with bioactive glass. Polymers (Basel). 2021;13(7): 1054.
https://doi.org/10.3390/polym13071054
[20] El-Adl ET, Ebaya MM, Habib ESE, Zaghloul NM. Comparative measurement of short-term fluoride release and inhibition of caries around restoration by ion-releasing restorative materials: An in vitro Sci Rep. 2025;15(1): 1600.
https://doi.org/10.1038/s41598-024-78918-x
[21] Kasraei S, Haghi S, Farzad A, Malek M, Nejadkarimi S. Comparative of flexural strength, hardness, and fluoride release of two bioactive restorative materials with RMGI and composite resin. Braz J Oral Sci. 2022;21: e225263.
https://doi.org/10.20396/bjos.v21i00.8665263
[22] Islam MS, Padmanabhan V, Koniali G, Alabdin MZ, Aryal AC, Hashim NT, et al., Fluoride release, recharge, and mass stability of restorative dental materials: an in vitro Dent J (Basel). 2025;13(10): 438.
https://doi.org/10.3390/dj13100438
[23] Aliberti A, Garcia-Godoy F, Borges ALS, Tribst JPM, Gasparro R, Ausiello P. Calcium, phosphate and fluoride ionic release from dental restorative materials for the elderly population: An in vitro Front Oral Health. 2025;6: 1609502.
https://doi.org/10.3389/froh.2025.1609502
[24] Temirek MM. Microanalysis for ions release of restorative materials used as posterior restorations. Egypt Dent J. 2025;71(1): 877-898.
https://doi.org/10.21608/edj.2024.329359.3238
[25] Ivica A, Salinovic I, Jukic Krmek S, Garoushi S, Lassila L, Sailynoja E, et al., Mechanical properties and ion release from fibre-reinforced glass ionomer cement. Polymers (Basel). 2024;16(5): 607.
https://www.mdpi.com/2073-4360/16/5/607
[26] Yeslam HE, Hasanain FA. Comparative analysis of flexural and compressive strengths of bioactive alkasite compared to other ion-releasing restorative materials. Biomimetics (Basel). 2025;10(11): 751.
https://doi.org/10.3390/biomimetics10110751
[27] Maaly T, Darweesh FA, Elnawawy MS. Ion release, microhardness and enamel demineralization resistance of new bioactive restorative materials. J Clin Exp Dent. 2025;17(6): e656.
https://doi.org/10.4317/jced.62357
[28] François P, Benoit A, Slimani L, Dufresne A, Gouze H, Attal JP, et al., In vitro remineralization by various ion-releasing materials of artificially demineralized dentin: A micro-CT study. Dent Mater. 2024;40(3): 520-6.
https://doi.org/10.1016/j.dental.2023.12.013
[29] Alambiaga-Caravaca AM, Chou YF, Moreno D, Aparicio C, Lopez-Castellano A, Feitosa VP, et al., Characterisation of experimental flowable composites containing fluoride-doped calcium phosphates as promising remineralising materials. J Dent. 2024;143: 104906.
https://doi.org/10.1016/j.jdent.2024.104906
[30] Ibrahim H, Aziz AA, Yahya NA, Yap AU. Surface degradation of ion-releasing restorative materials with cariogenic challenge. Oper Dent. 2024;49(2): 178-188.
https://doi.org/10.2341/23-038-L
[31] Abdelsalam AE, Ismail HS, Hamama HH. Elemental and micromorphological analysis of ion releasing restoration/carious dentin interface. Sci Rep. 2025;15(1): 30712.
https://doi.org/10.1038/s41598-025-13977-2
[32] Puttipanampai O, Panpisut P, Sitthisettapong T. Assessment of fluoride-releasing materials in remineralization of adjacent demineralised enamel. Appl Sci. 2025;15(4): 2077.
https://doi.org/10.3390/app15042077
[33] Llancari-Alonzo P, Alvitez-Temoche D, Ladera-Castaneda M, Castro-Ramirez L, Lopez-Gurreonero C, Cayo-Rojas C. Fluoride release and flexural strength of four ion-releasing restorative materials: An in vitro comparative study. J Clin Exp Dent. 2024;16(10): e1207.
https://doi.org/10.4317/jced.61818
[34] Garoushi S, Vallittu P, Lassila L. Development and characterization of ion-releasing fiber-reinforced flowable composite. Dent Mater. 2022;38(10):1598-1609.
https://doi.org/10.1016/j.dental.2022.08.006
[35] Garoushi S, Peltola T, Siekkinen M, Hupa L, Vallittu PK, Lassila L, et al., Retention of strength and ion release of some restorative materials. Odontology. 2025;113(2): 714-23.
https://doi.org/10.1007/s10266-024-01010-3
[36] Radwanski M, Zmyslowska-Polakowska E, Osica K, Krasowski M, Sauro S, Hardan L, et al., Mechanical properties of modern restorative bioactive dental materials: An in vitro Sci Rep. 2025;15(1): 3552.
https://doi.org/10.1038/s41598-025-86595-7
[37] Akkuc S, Duruk G, Keles A. Remineralization effect of three different agents on initial caries and erosive lesions: A micro-computed tomography and scanning electron microscopy analysis. BMC Oral Health. 2023;23(1): 106.
https://doi.org/10.1186/s12903-023-02805-6
[38] Wiegand A, Buchalla W, Attin T. Review on fluoride-releasing restorative materials–fluoride release and uptake characteristics, antibacterial activity and influence on caries formation. Dent Mater. 2007;23(3): 343-62.
https://doi.org/10.1016/j.dental.2006.01.022
[39] Nicholson JW, Sidhu SK, Czarnecka B. Fluoride exchange by glass-ionomer dental cements and its clinical effects: A review. Biomater Investig Dent. 2023;10(1): 2244982.
https://doi.org/10.1080/26415275.2023.2244982
[40] Tokarczuk D, Tokarczuk O, Kiryk J, Kensy J, Szablinska M, Dyl T, et al., Fluoride release by restorative materials after the application of surface coating agents: A systematic review. Appl Sci. 2024;14(11): 4956.
https://doi.org/10.3390/app14114956
Licensed
© 2026 Copyright by the Authors.
Licensed as an open access article using a CC BY 4.0 license.
Article Contents Author Wahaj Anees1, * 1Department of Forensic Sciences, Institute of Basic Medical Sciences- Khyber Medical University, Peshawar, Pakistan
Article Contents Author Danish Rahman1, * Matias Garcia-Constantino1 1School of Computing, Ulster University, Belfast Campus, BT151AP, United Kingdom Article History:
Article Contents Authors Saqib Hussain Hadri1, Muhammad Hassnain1,* , Aqsa Arshed1, Shamaiza Kousar1, Aleeza Yasmeen1, Nuzhat Latif1, Kiran Ijaz1, Maryam
Article Contents Author Amal S. Al Saadi1, * 1Sohar University, Sohar, Oman Article History: Received: 13 June, 2026 Accepted: 09
Article Contents Author Olabode Adeyemi David1, * , Nduka Christiana1, Akazue Ruth Chioma1, Amos Mishael1 1Department of Animal Production,
Article Contents Author Muzmmil Memon1, * 1Department of Computer Science Management, Avila University, Kansas City, Missouri, United States Article History: